Request a quote * = required field Cancel

Please fill out the form below to have a West Physics representative contact you to arrange for a service or product quote for your facility.

Our address and telephone numbers are:

West Physics
3825 Paces Walk SE
Suite 250
Atlanta, GA 30339

770-435-9186 • 1-866-275-9378 • FAX 770-599-2333

Office Hours: West Physics maintains liberal office hours for the convenience of our customers nationwide.

Monday-Friday:

9AM – 8PM Eastern Time
8AM – 7PM Central Time
7AM – 6PM Mountain Time
6AM – 5PM Pacific Time

Closed Weekends & U.S. National Holidays

Request a quote

Blog

The Expert in the Room

In radiology, knowing the answer is only the price of admission. The rarer skill is making that answer mean something.

SOMEWHERE this morning, a radiology director opened a service report on a CT scanner and found a number they didn’t recognize. It might be nothing. It might be the first sign of a problem that will take the scanner offline for a week, cancel dozens of patient appointments and draw the attention of an accreditation body. The report won’t tell her which. For that, she needs a person.

Modern imaging departments run on that kind of person: the physicists, engineers and specialists who understand the machinery, the magnets and X-ray tubes, yes, but also the thicket of regulations, accreditation standards, safety protocols and manufacturer guidance that surrounds them. As the technology grows more sophisticated, their knowledge becomes more essential. But ask the people who rely on them what separates a good expert from a great one, and the answer is rarely about how much they know. It’s about what they do with it.

The Four Questions

Real experts, it turns out, spend surprisingly little time proving how smart they are. Their gift is taking something complicated and making it understandable.

A hospital administrator facing a technical issue usually doesn’t need a seminar. She needs answers to four questions: Is this a problem? How serious is it? What should we do about it? And how fast?

Expertise earns its keep when it answers those questions clearly. An expert who can spot a problem but can’t explain why it matters hasn’t solved anything. They’ve simply handed the team a second problem. Figuring out what the first one means.

Signal and Noise

Few workplaces generate information at the pace of an imaging department. Equipment evaluations, service logs, quality-control results, regulatory updates, accreditation requirements, safety procedures and manufacturer recommendations all compete for attention, and each arrives looking equally urgent. The craft of expertise lies in knowing the difference between the routine and the alarming.

Anyone can read a number off a report. The expert knows what the number is saying.   

  1. Is it within the expected range?
  2. Has it drifted since last quarter?
  3. Is it an isolated quirk or the leading edge of something larger?
  4. Should someone keep an eye on it, or pick up the phone right now?

That judgment, call it context, is often worth more than the raw technical knowledge underneath it. The value isn’t in finding the information. It’s in understanding what the information means.

Lost in Translation

Every technical field develops its own dialect. Among specialists, it’s efficient shorthand. But it becomes a wall when the information has to reach administrators, physicians, technologists and others who are responsible for making decisions. Translating technical findings into plain language is a discipline of its own, and an underrated one.

The best version often sounds disarmingly simple: Here’s what we found. Here’s why it matters. Here’s what I’d do next.

That economy doesn’t erase the technical knowledge behind the recommendation; it demonstrates it. Making something complicated feel simple is one of the hardest things a specialist can do, and one of the surest signs they truly understand it.

The Pattern Library
Textbooks, standards and training can teach the rules. Experience teaches something harder to name: pattern recognition. A professional who has walked through hundreds of facilities, worked on hundreds of machines and lived through dozens of strange situations begins to sense when something is off before it is obviously wrong. They remember a similar case from years earlier. They know which questions to ask, because they have seen what happens when nobody asks them.

None of that fits neatly into a procedure manual. And paradoxically, it may matter more as the machines get smarter. Technology now produces more data than ever before. Expertise is what decides what to do with it.

Better, Not Beholden

There is one more test of a great technical expert: whether they leave the people around them more capable. They answer a question in a way that makes it easier to ask the next one. They explain the reasoning behind a recommendation instead of simply issuing a verdict. They share what they know and teach teams what to watch for. They don’t hide behind complexity as a show of authority.

Over months and years, a team that works alongside that kind of expert grows more confident and more knowledgeable. Expertise that leaves everyone else perpetually confused has fallen short, no matter how impressive it sounds in the meeting.

A Matter of Judgment

In the end, it comes down to judgment. Knowledge, training, credentials and experience all count, but their real value shows up only when they combine into something sound: knowing when an issue matters and when it doesn’t, when to dig deeper and when to act, and how to explain all of it to the people who have to decide.

Radiology will never run short of technical detail. What it will always need are people who can turn that complexity into clarity, and then turn that clarity into better decisions. For the director with the puzzling number on their desk, that is the difference between a worry and a plan.

Blog Form Survey Meter Calibration Service

Email(Required)


The Screen That Interrupts The Scan

CT technologist at a scanner console reviewing a dose notification with two clinicians

Inside the quiet moment when a CT machine asks a technologist to think twice and why that pause may be one of the most underappreciated safeguards in modern medicine

Every day, in thousands of hospitals and imaging centers, a small message appears on a computer screen in the seconds before a CT scan is acquired. It is not an emergency. It is not a malfunction. It is, in essence, a machine asking a human being to pause and think.

That pause has a name, several in fact. The terms are “dose notification” and “dose alert,” and though they are often used as if they mean the same thing, they don’t.

Ballerina balancing en pointe on a spotlit stage

A Balancing Act

Computed tomography occupies a critical place in medicine. The technology delivers cross-sectional images that can catch a tumor, confirm an internal bleed, or rule out a stroke in minutes and its speed and clarity has made it a backbone of emergency and diagnostic medicine. This technology, however, requires exposure to a small amount of ionizing radiation. While radiation exposure in diagnostic imaging generally stays at levels low enough that risk becomes genuinely difficult to quantify, it remains important to limit radiation exposure to be as low as reasonably achievable (ALARA).

That tension: enormous clinical value paired with a potential risk that must be minimized is what scanner vendors have developed these features to regulate. And within that system, two features do important day-to-day work keeping the balance: the notification and the alert.

Two Warnings, Two Moments

The difference between the two comes down to the scope and the type of action triggered. A dose notification can occur before each scan begins and is triggered when the parameters a technologist has planned are projected to exceed a facility’s chosen dose metric threshold for the type of scan being performed. It functions less like an alarm than a checkpoint: a built-in moment to double back and confirm that everything entered into the machine is correct.

A dose alert is more serious and is not tied to a particular type of scan. Rather than scrutinizing a single acquisition, it tracks the cumulative radiation expected across an entire examination and is relevant when a study includes multiple phases or body parts. While each scan or phase may individually have reasonable dose levels, it may add up to something larger for the patient as a whole. At this point a second opinion from a physician or manager is needed before the exam should continue.

Notifications ask: were the parameters for this acquisition configured correctly? Alerts require a supervisor to enter a administrator password to continue, documenting a named team leader who takes responsibility for the risk of proceeding with the exam. Treating them interchangeably, misses the point of having two systems at all.

Neither Is a Verdict

Perhaps the most important thing to understand about both warnings is what they are not: a permanent stop sign. A notification appearing on screen is not a declaration that harm is imminent, nor proof that a mistake has been made. Larger patients, unusual anatomy, and complex clinical indications can all justify parameters that exceed a standard threshold, and in those cases, the appropriate response is not to abort but to verify. Dose alerts are typically set at the level where harms such as a radiation induced skin burn start to become theoretically possible, which makes the decision to proceed a clinical decision beyond the scope of a floor technologist. This is why the scanner requires the permission of a clinician, who can weigh the risk against the necessity of the scan, to continue.

The danger runs in both directions. Technologists who treat every warning as an absolute limit risk delaying or denying medically necessary care. Technologists who grow numb to warnings clicking through them reflexively, lose the safeguard entirely. That second failure mode has a name familiar to anyone who has worked around alarm-heavy systems: alert fatigue. It is, in the world of CT dose management, the quiet enemy.

The goal, then, is neither blind compliance nor blind dismissal. It is a genuine decision point where a person must look at what triggered the message before deciding what to do next.

Scattered three-dimensional numbers on a dark background

The Numbers Behind the Warning

None of this works if the thresholds themselves are wrong. Set a notification value too conservatively, and it fires so often that staff tune it out. Set it too loosely, and it fails to catch the outlier case it exists to flag. Maintaining appropriate thresholds as equipment, protocols, and patient populations shift, becomes essential.

The measure of success is a machine that speaks up exactly when it should, and is trusted and taken seriously when it does.

Glowing blue data charts showing trends over time

From Pop-Up to Pattern

Forward-looking imaging programs are starting to treat these warnings as more than momentary interruptions to be dismissed and forgotten. Logged over time, notifications and alerts become data. A record that can reveal whether a particular protocol keeps tripping the same threshold, whether one scanner generates disproportionately more warnings than another, or whether staff are routinely overriding an alert for the same recurring clinical reason.

Read that way, a warning stops being a nuisance and becomes a diagnostic tool of its own, pointing not at the patient, but at the protocol, the equipment, or the workflow that produced it.

Team members stacking their hands together in a show of unity

Culture, Not Just Configuration

Ultimately, no amount of software can substitute for a well-trained, well-supported staff. Technologists need to know not just that a warning might appear, but why it exists, what triggered it, and what is expected of them when it does. Clear written procedures, ongoing education, and a culture that treats an unexpected alert as worth investigating, and not simply clearing, are what make the technology meaningful.

Done right, the system achieves something genuinely difficult and important: it protects patients from unnecessary radiation exposure without standing in the way of the imaging clinicians need to do their jobs.

The message on the screen is not the final word. The real safeguard is what happens next: a trained professional recognizes the signal, understands its meaning, and makes an informed decision. Repeated thousands of times each day, these moments may seem routine, but they are anything but insignificant. They are where technology, expertise, and accountability come together—and where a strong culture of radiation safety is ultimately built.

Blog Form Survey Meter Calibration Service

Email(Required)

Beyond the Annual Survey: How the Modern Medical Physicist Is Transforming Patient Care

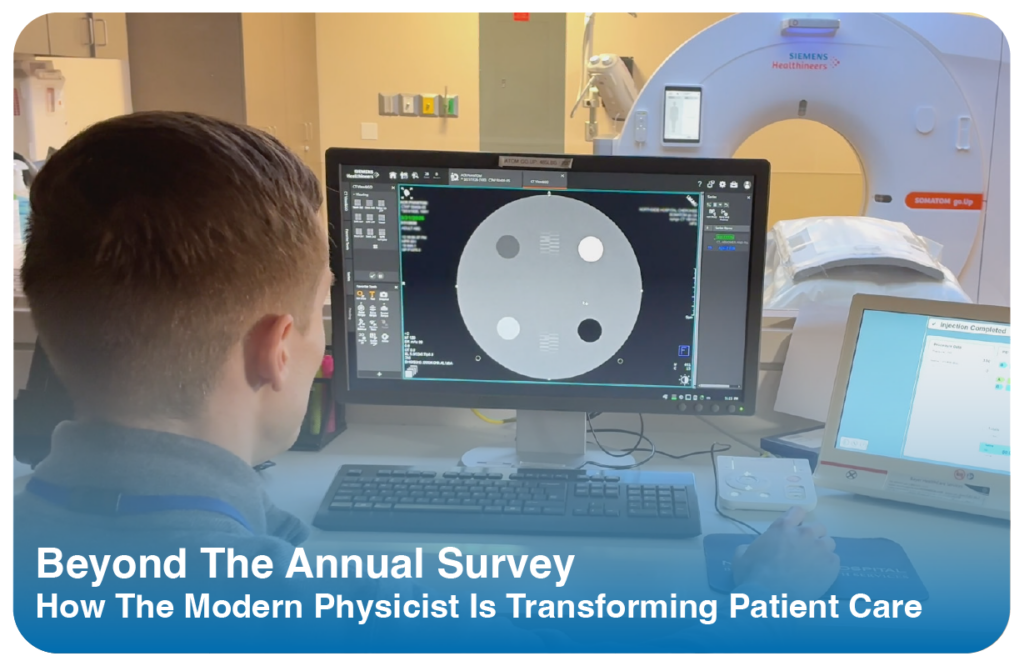
Medical physicist reviewing CT phantom images at a scanner console

For decades, the medical physicist was often viewed as the behind-the-scenes technical expert. The person who arrived after hours, tested imaging equipment, completed required reports, and moved on to the next facility. Those traditional responsibilities remain essential, but the role of the medical physicist has changed significantly.

Today, medical physicists are increasingly integrated into the clinical environment. They work alongside radiology leaders, radiologists, technologists, IT teams, safety professionals, and other hospital departments to improve imaging quality, optimize radiation dose, strengthen safety programs, evaluate new technology, and support better patient care. As medical imaging has become more complex, the physicist has evolved from primarily a compliance resource into an important clinical partner.

Typewriter labeled then beside a laptop labeled now

Why the Physicist’s Role Has Changed

Traditionally, diagnostic medical physicists have been responsible for radiation shielding designs, shielding integrity surveys, equipment acceptance testing, periodic physics testing, radiation safety activities, personnel dosimetry, and quality control program oversight.

Those responsibilities have not disappeared, but the scope has expanded.

The growth of advanced imaging technologies such as CT, MRI, PET/CT, and SPECT/CT has introduced new technical and safety considerations. At the same time, increasing imaging volumes, accreditation requirements, regulatory oversight, highly publicized radiation overexposure events, and workforce challenges have pushed medical physicists into a more active role within imaging departments.

The result is a different model of medical physics. One based on collaboration rather than periodic inspection.

Moving From Dose Reduction to Dose Optimization

One of the clearest examples of this expanded role is CT dose optimization.

It can be tempting to think that reducing radiation dose is always the goal. But reducing dose too aggressively can compromise image quality. The real objective is to find the appropriate balance between radiation exposure and the diagnostic information the radiologist needs.

Medical physicists can use phantom testing to evaluate changes in parameters such as kV and mAs and determine how those adjustments affect contrast and noise before changes are introduced clinically. Just as importantly, protocol changes should involve the radiologist so that technical improvements do not come at the expense of diagnostic quality.

Physicists can also help imaging departments make sense of the enormous amount of information generated by dose-tracking systems. A value that appears to be a dose outlier, for example, may actually be the result of how the scanner calculated or reported the dose rather than an actual problem with the examination. For example, a routine head examination can appear as an outlier because a change in scan field of view and bow-tie filter resulted in the dose being reported using a different phantom size.

That distinction can prevent teams from spending time investigating a problem that does not really exist.

Rolled architectural blueprints for imaging facility design

Bringing Physics Into Equipment Selection and Facility Design

The physicist’s value can begin long before a new scanner treats its first patient.

When facilities purchase imaging equipment, physicists can help interpret manufacturer specifications, evaluate hardware and software safety features, consider upgrade paths, assess radiation exposure factors, and identify limitations that may not be obvious during the purchasing process.

Their involvement can be equally valuable during construction and room design.

Consider something as simple as the placement of a chest bucky. Putting it against a wall with a highly occupied office on the other side may create unnecessary shielding challenges. In MRI, the location of the control room can affect whether the technologist has a clear view of the entrance to Zone 4. Nuclear medicine and PET departments introduce another consideration: how radioactive material and patients will safely move between hot labs, uptake rooms, and imaging areas.

These decisions demonstrate why physics involvement should occur during planning, not after construction has been completed.

Clinical staff working in a hospital hallway

Expanding the Safety Conversation Beyond X-Ray

The modern medical physicist’s safety responsibilities can also extend beyond traditional ionizing radiation.

MRI is one particularly important area. Medical physicists can help establish appropriate MRI zones, evaluate access controls, review signage, measure magnetic field boundaries, assess MR-conditional equipment, and develop policies that protect patients and staff.

The importance of these processes becomes especially clear during an emergency.

MRI safety has become a major focus specifically of Joint Commission surveys, making the medical physicist an important resource for identifying potential risks and strengthening safety programs. Physicists can assess policies and procedures, signage, MRI zone layouts, access controls, the 5-gauss line, and MR-conditional equipment. They can also provide valuable input when designing new MRI spaces, including ensuring technologists have clear visibility and control of Zone 4 access. Regular MRI environment audits and proper documentation help facilities identify issues early, improve clinical workflow, and remain prepared for Joint Commission surveys.

In other words, MRI safety is not simply about having the right sign on the door. It requires a functioning safety system that staff can follow when something goes wrong.

Laser safety is another area where medical physicists can play an important role. Although surgical lasers present different risks than diagnostic X-ray equipment, they still require appropriate policies, training, protective eyewear, equipment inventories, and ongoing safety oversight. Even a seemingly simple oversight can create risk. For example, storing protective eyewear for lasers with different wavelengths together without clear identification can lead staff to select glasses that provide little or no protection for the laser being used.

That is exactly the type of hidden vulnerability a structured physics-led safety program can uncover.

Medical care team in white coats and scrubs

A Clinical Partner, Not Just a Compliance Requirement

Perhaps the biggest change in medical physics is not a new test, regulation, or technology, although those do exist. It is a change in how the physicist fits into the healthcare team.

The physicist increasingly acts as a technical translator, connecting the engineering behind imaging technology with the realities of clinical care. That requires understanding not only how a scanner works, but also how technologists use it, what radiologists need from the resulting images, how patients move through the department, and how technical recommendations affect daily operations.

That perspective can be particularly valuable as imaging departments face increasingly sophisticated technology with fewer available resources.

The days when the physicist simply arrived overnight, tested equipment, and left a report behind are disappearing. Modern medical physics is increasingly built around ongoing collaboration with the staff responsible for imaging operations and patient care.

By involving medical physicists in equipment selection, facility design, dose optimization, accreditation, MRI and laser safety, staff training, and clinical workflow, organizations can move beyond a once-a-year compliance mindset. Medical physics becomes an ongoing part of the safety program, helping imaging teams make informed decisions, strengthen clinical practices, and ultimately support better patient care.

Blog Form Survey Meter Calibration Service

Email(Required)

Building a Calibration Program That Protects Patients, Staff, and Compliance

Introduction

You’ve learned why calibration matters, how to address common pain points, and how to align calibration with your operational needs and documentation processes. Now it’s time to pull it all together into a calibration program that strengthens your entire radiation safety culture.

Survey meter calibration is not simply a compliance checkbox; it is a foundational tool for ensuring accurate dose monitoring, safe patient care, and staff protection. A structured calibration program ensures your meters work when you need them most—without last-minute scrambles, lost certificates, or unreliable readings.

Best Practices Recap: The Pillars of a Strong Calibration Program

To build a calibration program that enhances safety, operational reliability, and compliance, implement these proven practices:

  • Maintain an Accurate Meter Inventory
    Document each meter’s serial number, type, location, and primary use case. This inventory serves as your calibration control center, allowing you to track due dates, identify needs, and plan rotations efficiently.
  • Rotate Calibration Schedules to Minimize Downtime
    Avoid having all your meters out for calibration simultaneously by staggering due dates across your fleet. Keep backup meters available to ensure operational readiness during calibration cycles.
  • Align Calibration with Use Cases and Energy Ranges
    Calibrate meters at energy levels relevant to your clinical operations (e.g., low-energy calibration for I-125, mid-energy for diagnostic X-ray, high-energy for LINAC QA). This ensures your readings reflect true conditions in your facility, not just lab conditions.
  • Perform Daily/Weekly Constancy Checks
    Regular constancy checks with a check source allow you to catch drift or malfunction between annual calibrations, ensuring your meters remain accurate and operational year-round.
  • Store Calibration Certificates Digitally
    Request electronic certificates from your calibration vendor and store them in a centralized, searchable digital folder by serial number. Integrate calibration due dates into your compliance calendar for proactive planning.
  • Train Staff on Meter Use and Limitations
    Calibration is effective only if meters are used correctly. Train your team on:
  • Pre-use operational checks.
  • Battery management.
  • Understanding meter limitations, especially regarding energy dependence and geometry effects.

These best practices turn calibration from a compliance hassle into a reliable foundation of your safety culture.

Case Study: A Regional Healthcare System’s Transformation

A regional healthcare system recently implemented these steps to overhaul a disorganized calibration process that frequently triggered stress during audits and left staff uncertain about meter reliability.

What They Changed:

  • Conducted a meter inventory audit, tagging each unit and logging it into a digital tracker.
  • Staggered calibration due dates and established a rotation schedule.
  • Requested multi-energy calibration matching operational needs, particularly for their nuclear medicine departments.
  • Added monthly constancy checks to their safety program, with results logged for trend monitoring.
  • Transitioned all calibration records to a searchable, cloud-based compliance folder.
  • Provided refresher training to staff on meter use and checks.

Results:

  • Reduced downtime during calibration cycles, maintaining operational readiness across all departments.
  • Passed state and accreditation audits with zero findings, impressing regulators with their documentation readiness.
  • Improved staff confidence in meter readings, enhancing radiation safety during patient care and environmental monitoring.
  • Identified and replaced two meters showing drift before they could impact safety or patient release decisions.

By transforming calibration from a reactive task into a proactive program, the facility strengthened safety, reduced operational stress, and elevated compliance readiness.

Calibration is Safety AND Compliance

Calibration is not just about getting a sticker or satisfying an inspector. It is about ensuring your meters provide accurate, actionable data when you are making decisions about patient care, staff exposure, and environmental monitoring.

A structured calibration program:

  • Protects patients by ensuring safe care and accurate dose monitoring.
  • Protects staff by providing reliable exposure assessments in real time.
  • Protects your facility’s compliance posture, reducing risk during audits and inspections.

Are you ready to transform your survey meter calibration program into a strength rather than a stressor?

Whether you are a hospital, imaging center, or industrial facility, you can implement these strategies to build a calibration program that enhances safety and operational reliability while ensuring compliance.

Let’s discuss how your facility can:

  • Establish a robust calibration rotation.
  • Align calibrations with your operational energy ranges.
  • Transition your documentation to digital, audit-ready systems.
  • Train your staff for a culture of radiation safety and meter readiness.

Blog Form Survey Meter Calibration Service

Email(Required)